The Mechanism Both Drugs Share
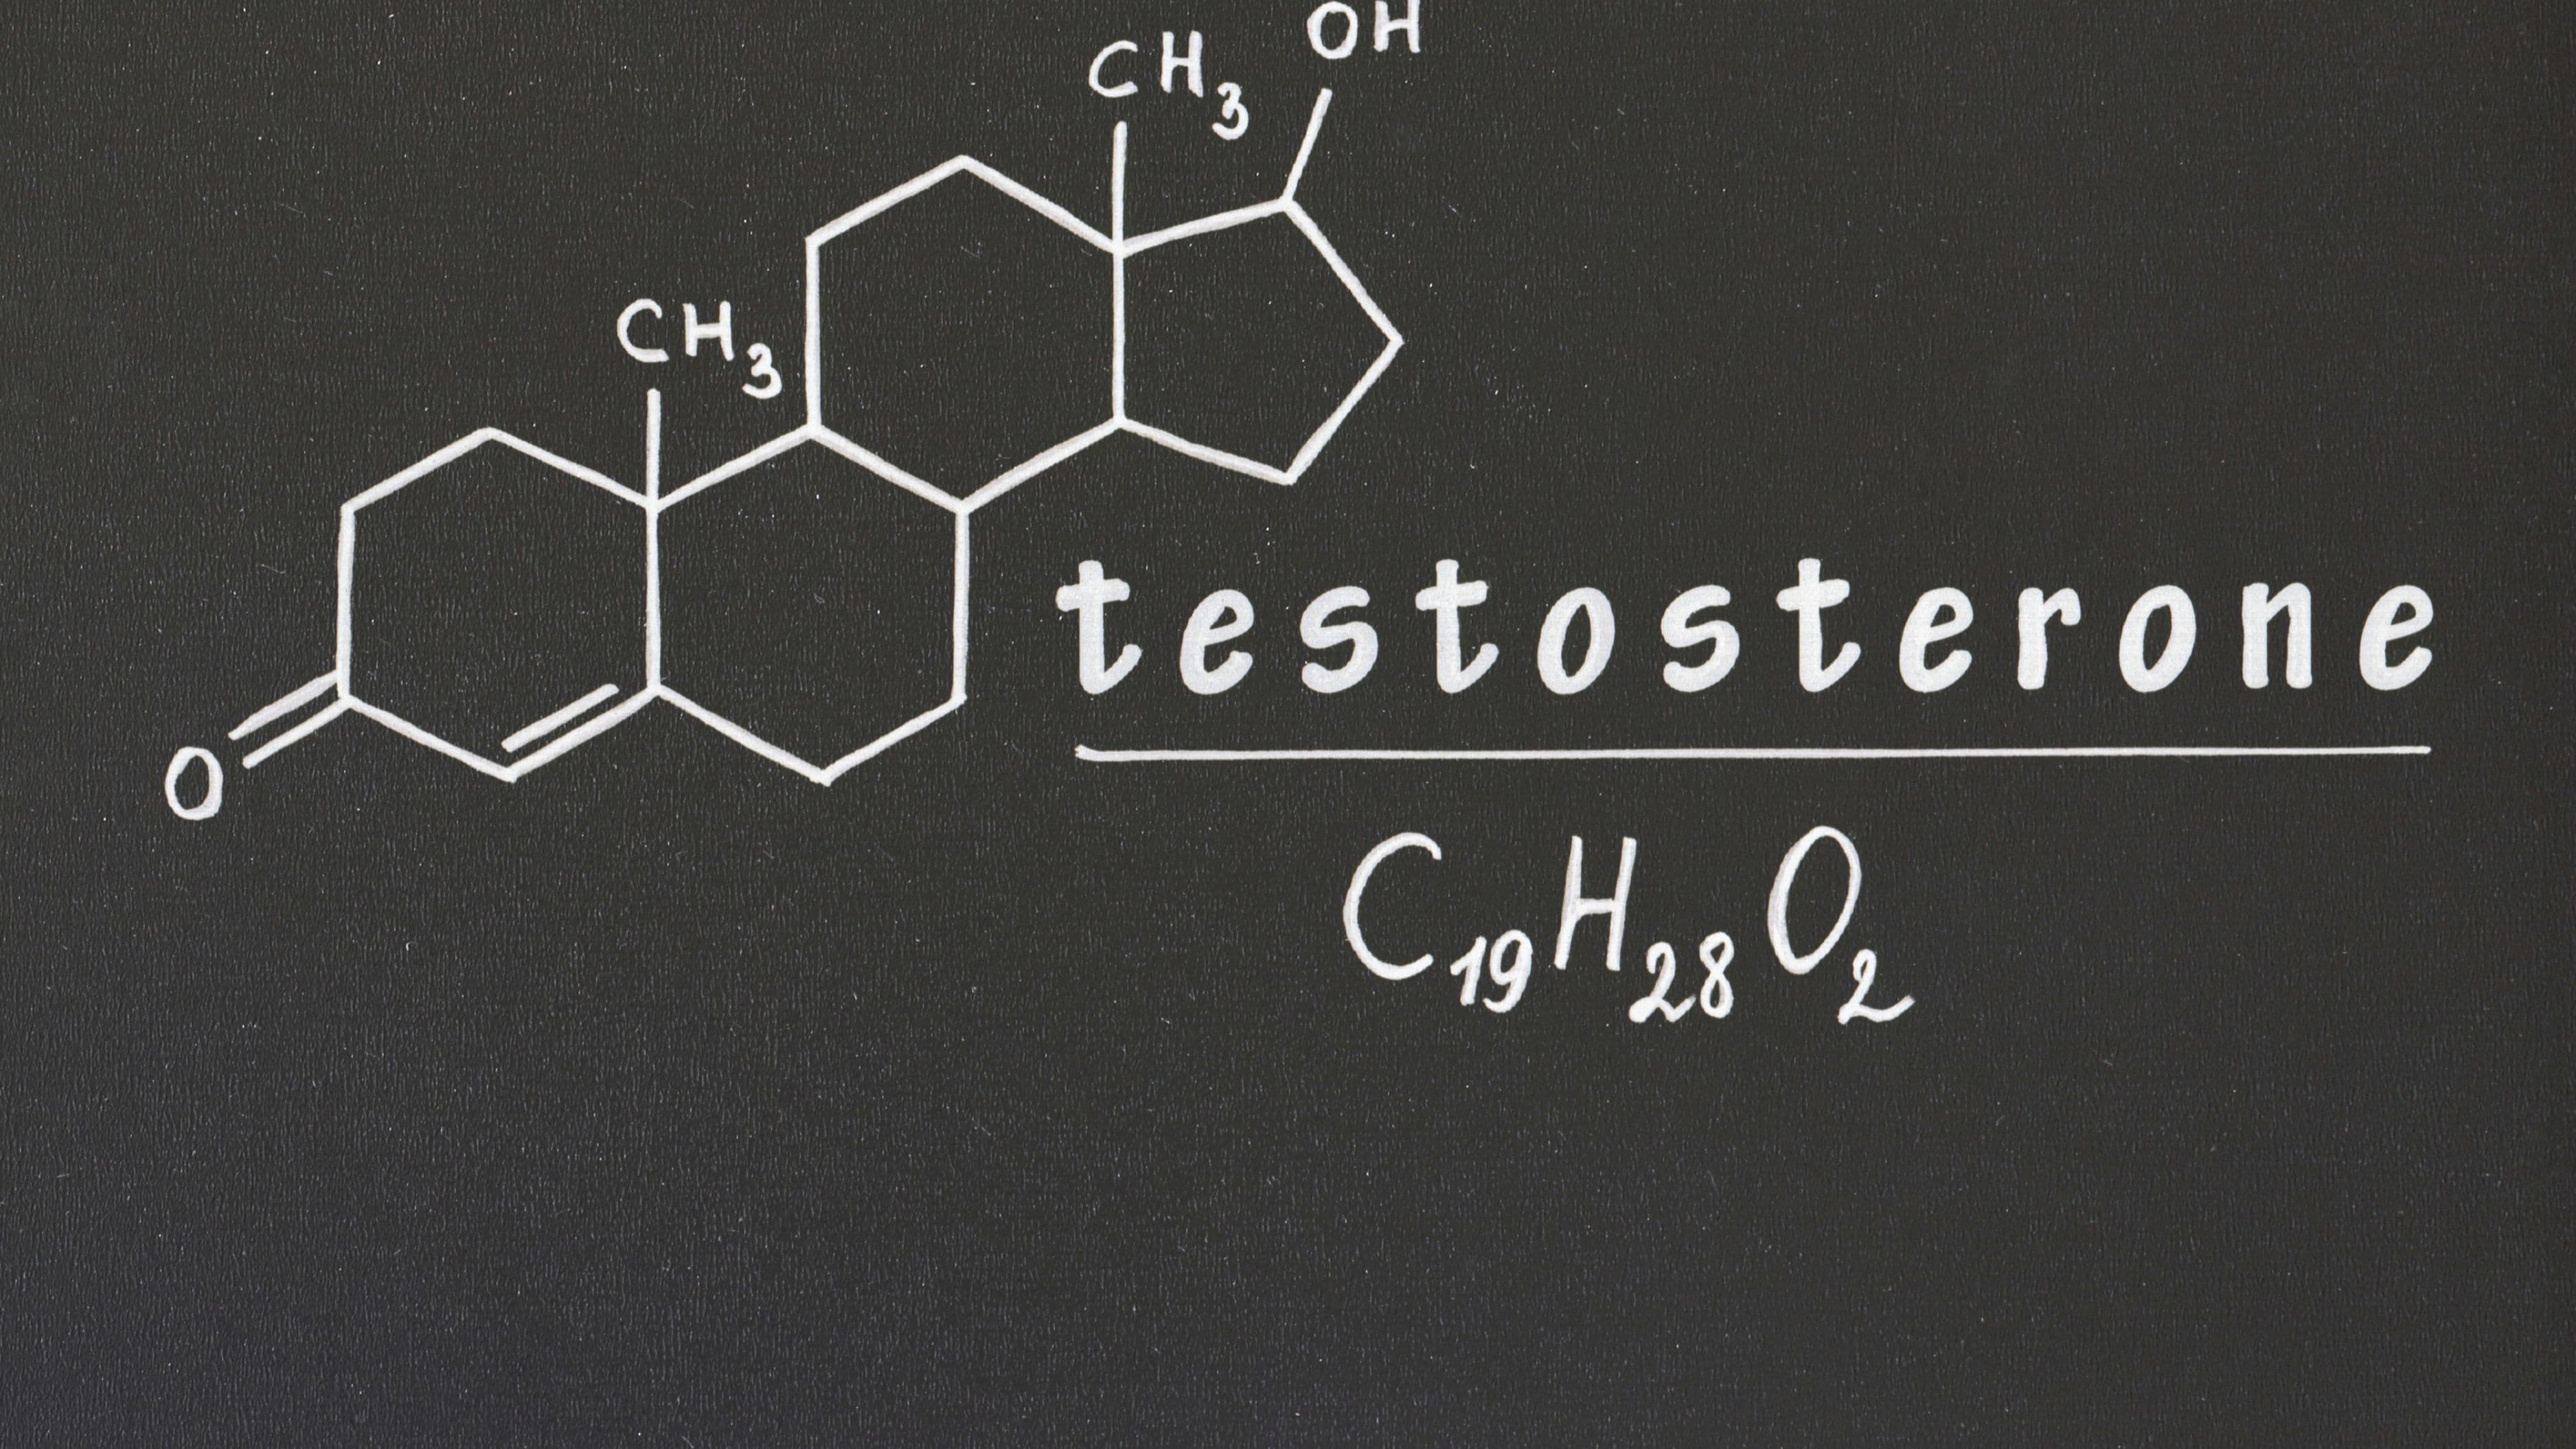
Clomiphene citrate is a selective estrogen receptor modulator (SERM) made up of two isomers: enclomiphene and zuclomiphene. Both drugs work the same fundamental way, by blocking estrogen receptors in the hypothalamus. The hypothalamus reads reduced estrogen signaling as a cue to increase GnRH output, which drives up LH and FSH from the pituitary, which in turn signals the testes to produce more testosterone. Unlike exogenous testosterone, this route keeps the entire HPG axis functioning rather than suppressing it, which is why SERMs are used both as a standalone protocol and as part of post-TRT recovery.
The critical difference is composition. Standard Clomid contains both isomers. Enclomiphene isolates only the trans-isomer, the one primarily responsible for the estrogen receptor antagonism that drives the testosterone increase.
Where Zuclomiphene Comes In
Zuclomiphene, the isomer left out of enclomiphene, behaves differently. It has a much longer half-life than enclomiphene, estimated at roughly 30 days compared to enclomiphene's roughly 10 hours, and it appears to have some estrogenic agonist activity of its own rather than purely blocking estrogen receptors. That combination, a long-acting compound with estrogen-like activity, is the leading theoretical explanation for many of the side effects historically associated with Clomid: mood changes, visual disturbances, and a general sense of "feeling off" that a meaningful subset of users report.
Because enclomiphene removes zuclomiphene from the equation, the theoretical case for fewer mood and visual side effects, and a shorter, more predictable clearance from the body, is mechanistically sound. This is the basis for most of the "enclomiphene is safer" claims circulating in performance and TRT-adjacent communities.
What the Evidence Actually Shows
The mechanistic argument is stronger than the clinical evidence backing it up. Enclomiphene has been studied specifically for raising testosterone in men with secondary hypogonadism, with trial data showing meaningful increases in LH, FSH, and total testosterone while generally preserving sperm parameters better than exogenous testosterone would. Comparative head-to-head trials directly measuring side effect rates between enclomiphene and full clomiphene citrate in men, at matched doses, over meaningful timeframes, remain limited.
That gap matters. It means the "enclomiphene is safer" claim rests more on plausible mechanism and isolated case reports than on large, controlled comparative trials. It's a reasonable hypothesis with real biological grounding, not a settled clinical fact. Men considering either option should treat the safety comparison as probable rather than proven.
Side Effects Reported With Both Compounds
Both enclomiphene and clomiphene citrate carry an overlapping side effect profile, since they share the same core mechanism. Reported effects include mood changes, visual disturbances (a rare but documented effect of clomiphene, warranting immediate discontinuation and evaluation if it occurs), hot flashes, and in rare cases, ovarian-hyperstimulation-like effects in women (clomiphene's original approved use is for female infertility, and it carries an FDA boxed warning in that context). In men, headaches and mild gastrointestinal upset are also reported with both compounds.
Blood work changes worth monitoring on either compound include estradiol, which typically rises alongside testosterone since more testosterone means more aromatization substrate, and liver enzymes, given that SERMs are hepatically metabolized.
Practical Considerations Beyond Safety
Cost and access differ meaningfully between the two. Clomiphene citrate is an older, generic, FDA-approved medication (for female infertility, with off-label use in men) and is widely available and inexpensive. Enclomiphene, while extensively studied, has faced a longer and more complicated path to full FDA approval for male hypogonadism in the United States, and is more commonly obtained through telehealth platforms or compounding pharmacies, often at a higher price point.
Dosing protocols also differ. Enclomiphene is typically dosed once daily given its shorter half-life, while clomiphene citrate protocols vary more, sometimes dosed every other day given zuclomiphene's long clearance time.
Who Might Consider Which Option
Men who tolerated Clomid poorly in the past, particularly with mood or visual side effects, have a reasonable mechanistic argument for trying enclomiphene instead, given that zuclomiphene is the most likely driver of those specific effects. Men with no prior negative experience on Clomid, and for whom cost or access to enclomiphene is a barrier, don't necessarily need to switch based on safety alone, since the comparative evidence isn't conclusive enough to call standard Clomid clearly unsafe at appropriate doses.
What to Avoid
Don't start either compound without baseline bloodwork, including LH, FSH, total and free testosterone, and estradiol, and don't continue past four to six weeks without a follow-up panel to confirm the intended response. Don't treat "enclomiphene is safer" as an established fact when evaluating cost or accessibility trade-offs, since the comparative safety data is still developing. Don't ignore visual disturbances on either compound, they warrant stopping the medication and contacting a physician. And don't source either medication outside a legitimate prescribing pathway with physician oversight and lab monitoring.
This article is for informational purposes only and is not a substitute for personalized medical advice. Any decision to start, switch, or stop a SERM protocol should be made with a physician who can review bloodwork, medical history, and treatment goals directly.
📚 Sources
National Library of Medicine, "Enclomiphene Citrate for the Treatment of Secondary Male Hypogonadism" – https://pubmed.ncbi.nlm.nih.gov/
FDA, Clomiphene Citrate Prescribing Information – https://www.accessdata.fda.gov/drugsatfda_docs/label/
Endocrine Society, "Testosterone Therapy in Men with Hypogonadism: An Endocrine Society Clinical Practice Guideline" – https://www.endocrine.org/clinical-practice-guidelines/testosterone-therapy-men-hypogonadism